Industries / Healthcare
Improving at the speed of thought.
The difference between good healthcare organizations and great ones is the ability to build the capability of people to improve the flow of material, information, and cost. Not to buy that capability, and not to merge with it.
Documented, Meritus Health
- 95% under 20 minutes Door to treatment in the Emergency Department after the patient flow redesign. Meritus Health
- Zero left without being seen On most days, ranging between none and two, in a department where the figure had never been near zero. Meritus Health
- 25% fewer psychological admissions A consequence of addressing care delays and supporting earlier medication intervention. Meritus Health
- No new wing built The department had asked for more rooms. The budget outside salaries was virtually zero, and no construction was required. Meritus Health
Sources: the transformation was the subject of a keynote at the 3rd annual Kata Summit in February 2017, given by Joseph Ross, then chief executive of Meritus Health. It was also written up by the Lean Enterprise Institute in Lean Transformation: Have You Hit the Lean Plateau? and in AME Target Magazine, October 2017, page 20.
The engagement
Reviving a transformation that had stalled.
Meritus Health is a 3,000 employee regional health system in Hagerstown, Maryland. It had been doing lean for five years, largely through five-day events and A3 projects, and had hit the plateau that almost every serious improvement program hits.
Craig joined as Operations Improvement Director in 2015, reporting first to the VP of Quality and later directly to the CEO through an executive transition.
The first attempt started at the department level, aiming at the organizational challenge of getting patients home on time. It turned into something more useful almost immediately. The nurses could not get home on time either. They could not reliably take an uninterrupted lunch.
So the goal changed to lunch on time. Proactively understanding and removing the burdens on the staff first rebuilt trust that had been lost, and it did something the original goal could not have done: it made the improvement system credible to the people who had to run it. That unit set the pattern for the rest of the organization.


Invite, do not assign.
Within the senior leadership team we identified an advance group of volunteers who wanted to move from a culture of present and decide to one of experiment, collaborate, and learn. Inviting rather than assigning had an effect nobody planned for: other senior leaders felt left out and asked to join.
That is the diffusion principle doing its job. Start with the people who are already leaning forward, let them produce a result, and the rest follow on evidence instead of instruction.
The two halves eventually met in the middle. Daily problem solving at the unit level joined to senior leader rounding, forming a structured feedback loop that kept the organization aware and aligned. The system held through subsequent executive turnover, which is the only real test.
One early lesson is worth stating plainly, because it cost us months: we taught that new habits require frequent practice with a coach, while our own most experienced coaches stayed in their established routines. Nothing changed until that did.
The Emergency Department
Redesigning patient flow with 3P.
Beginning in spring 2016, the ED team combined 3P design with daily improvement cycles. A benchmarking visit to Lehigh Valley Health Network's direct bedding model shaped the approach, and Lehigh Valley later used what came out of the Meritus work to improve their own.
The department needed more rooms. Waits of several hours were normal, and the instruction from the chief executive was, in his words, that we could do whatever we wanted as long as it did not cost any money. So the first move was to go and look. Even on the busiest days several rooms sat empty, always in the same section: eight rooms that had been optimized exclusively for abdominal complaints, known internally as the gut pain unit. Reconfiguring those helped, and the department still needed more rooms, which was the point at which it became clear the problem was not rooms.
Two phrases did most of the work from there. No harm, no wait, which is the manufacturing idea of perfect quality, one-by-one flow and no delay, translated into something a clinician can actually aim at. And we love empty beds, because an ED bed is the most contested real estate in a hospital, so the objective is to free one the moment a patient no longer needs it, and never to put a patient in one who never did.
The first story is the best story
By the time a patient finally sees a physician, they are often telling their story for the fourth time, and the first telling was the most detailed. The design directs patients to a bed or a chair so that the first time they tell it, they are telling the treatment provider.
Keep vertical patients vertical
Why put every patient in a bed when many do not need one and are more comfortable in a chair? If they are ambulatory, keep them ambulatory. Beds are used when a bed is what the patient needs, which also solves the room turnaround problem that beds create.
Design for the hardest case
The team started by mapping the most common patient type, then changed approach. Every patient is unique but the diagnostic tasks are not. Designing around a chest pain or shortness of breath presentation, which needs the full set of resources, meant simpler journeys could be tested by skipping steps. A long bone fracture follows the same sequence without the EKG.
Model a heavy day, not an average one
Capacity was modeled on a day in the top 20 percent of the year for volume. Designing around an average day guarantees being overburdened half the time, and it is much easier to take capacity out than to add it. That calculation sized the Rapid Assessment Zone.
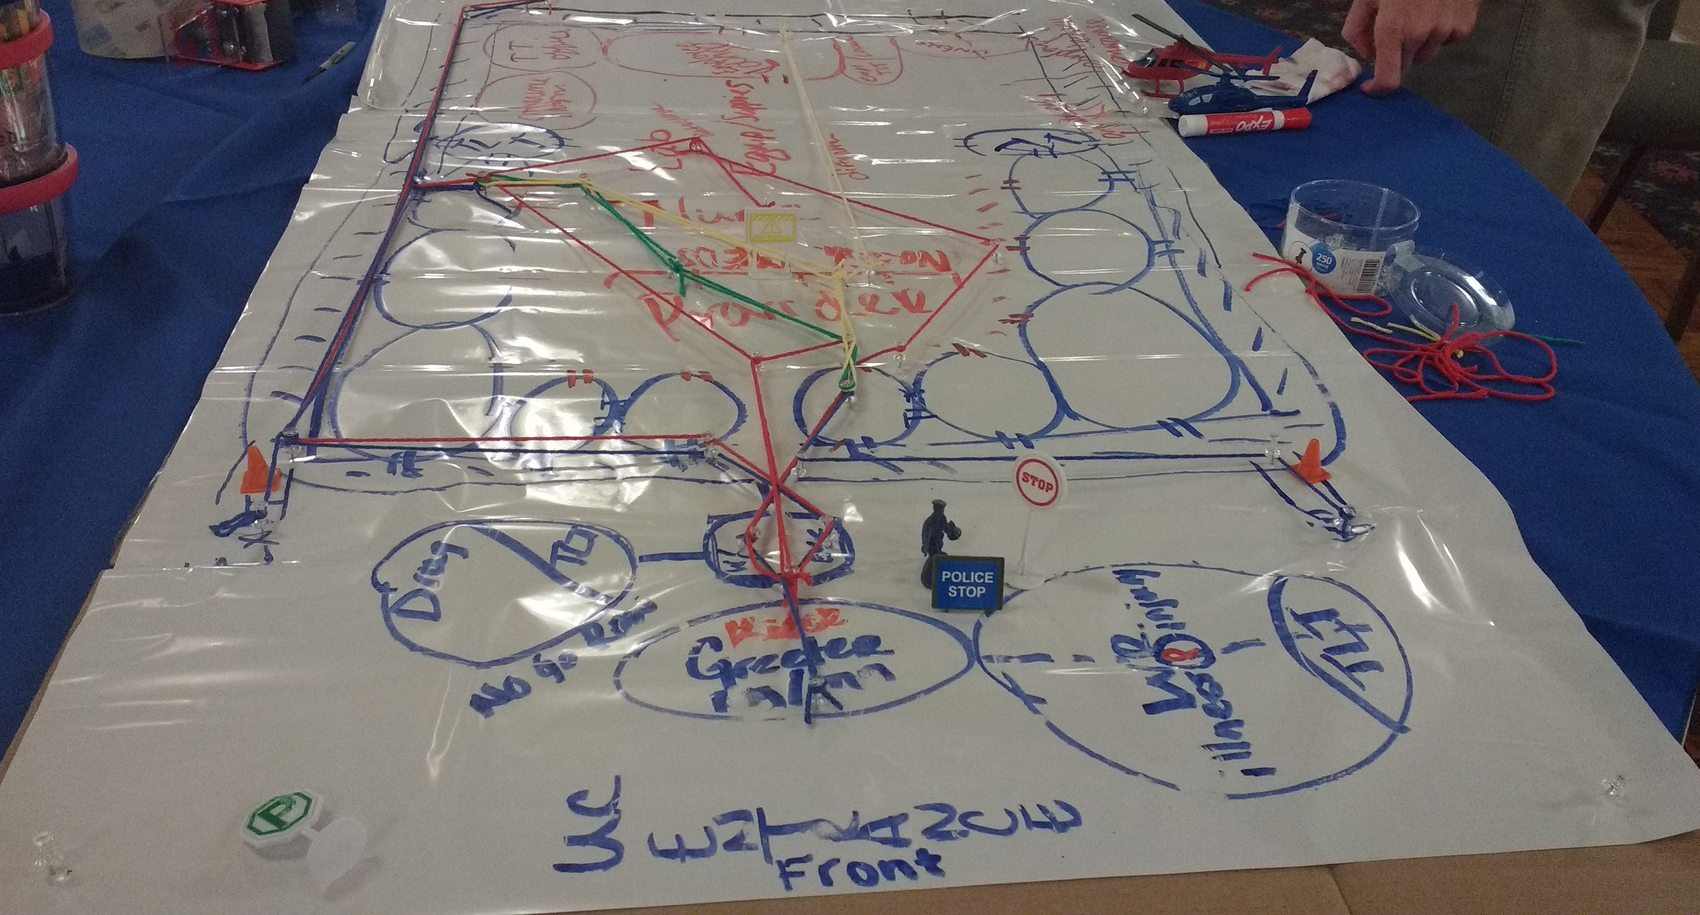
Two artifacts carried the design. A tabletop simulation, where the actual patients from that heavy day were moved through the proposed layout with markers and figures until the sequence held. And a process-at-a-glance: every step of the journey across the top, and for each one, who is required, what tasks and skills it needs, what information and equipment and supplies, what signals it, when to escalate, what medications are involved, how completeness is measured, what the space itself has to be like, and how long the step should take. Filling that grid in is where most of the arguing happens, and it is far cheaper than arguing on the day.


Implementation then ran as live pilots, and the pilot schedule is worth stating exactly because the discipline is the method. The first pilot was planned for two hours and stopped after thirty minutes, deliberately, to build countermeasures against what had just been learned. The second was planned for two hours and ran two. The third was planned for four and ran eight, because it was going well enough to leave on. Second shift arrived to an empty waiting room and asked whether it had been a slow day. It had not.
On pilot days obstacles were logged on flip chart pages as they appeared and crossed off as rapid experiments resolved them. After a few weeks the same sequence ran again for nights, which surfaced some firmly held and entirely wrong assumptions about how the department operated after dark. The by-product was better communication between shifts.
What a patient met at the end of it: enter, and go straight to the first free room in a ten-room Rapid Assessment Zone, each holding both a bed and a chair. Tell your story once, to a physician and nurse working as a pair, during the examination and a quick registration. The order goes in, the pair moves to the next patient, and a medication nurse follows up. Registration is completed by a mobile technician wherever you happen to be. Diagnostics run in a fixed sequence, so anyone walking the department can see a bottleneck at a glance. Patients finishing treatment who no longer need a bed wait in a partitioned Results Waiting Area with a nurse present, rather than occupying a room in order to finish an IV.
The most valuable thing the new process gave the team was not a number. It was visibility: for the first time the ED could see volume building through the day and what it would take to stay ahead of it. Bringing a second provider in at 11am, we could now see, already put the department in a deficit by the time they arrived.
Nothing about how a clinical task is performed was changed. The tasks were the same tasks. What changed was when each one happened, and in what order, which is what harmonizing a flow actually means in practice.
The work was presented at AME and at the Emergency Nurses Association, the department became a site other hospitals toured, and the team ended up advising Lehigh Valley on problems Lehigh Valley was still working through. The most common patient complaint afterwards was that the visit had been too quick to qualify for a meal ticket.
From the engagement
What the work looked like.



Also at Meritus
Three more pieces of the same system.
Real time problem reporting
In collaboration with MIT professor Steven Spear, Meritus became the first healthcare organization to pilot a real time issue reporting system, adapting the idea of stopping the line for a hospital setting. Front line staff could raise a problem from a phone in one touch and flag whether it needed immediate help.
The interesting result was not the tool. Paired with an organizational dashboard, it forced real time conversations between departments that had been pointing fingers at each other, because now everyone was looking at the same data about the same root cause.
A problem nobody was looking for
Piloting the same system with Facilities Engineering surfaced something no one had asked about: the engineers sat physically far from where most issues occurred, and response times reflected it. Moving where the team sat cut average response time by roughly 75 percent.
That is a good illustration of the method. Nobody set out to solve it. The system made it visible and the fix was almost free.
3P beyond the ED
The same design method built a cancer center with a healing garden, private spaces for chemotherapy patients, and streamlined radiation flow, and a multidisciplinary care clinic that eliminated waiting rooms for phlebotomy and primary care while improving how material and information moved between providers, specialty clinics, and the lab.
Yukon-Kuskokwim Health Corporation
Rural Alaska, where the nearest alternative is a flight.
Before the health system work, Craig was Sub-Regional Clinic Manager for Yukon-Kuskokwim Health Corporation, the tribal health organization serving villages across the Yukon-Kuskokwim Delta in western Alaska.
He ran a comprehensive rural outpatient and urgent care facility: radiology, laboratory, billing and coding, maintenance, environmental services, dental, and registration. It is the opposite constraint from a 300-bed hospital. There is no second site to escalate to, resupply is a scheduled flight rather than a truck, and a stockout is not an inconvenience.
Two things from that work outlasted the posting. A kanban card ordering system for pharmaceuticals and supplies, built for a place where reordering by someone noticing is not good enough, was later implemented across the sub-regional clinic system. And a barcode scanning system interfaced with the electronic health record cut patient registration time in half.
Separately, at Skagit Regional Health, a root cause analysis of medication errors uncovered a defect in the EHR itself, one that could have led to double dosing. It was resolved with the vendor. Selection and installation are the beginning of an EHR implementation, not the end. Organizations without strong problem solving at every level end up dependent on prolonged on-site vendor support, with frustrated staff, cost overruns, and real patient safety risk.
What the system produced
Not our projects. Theirs.
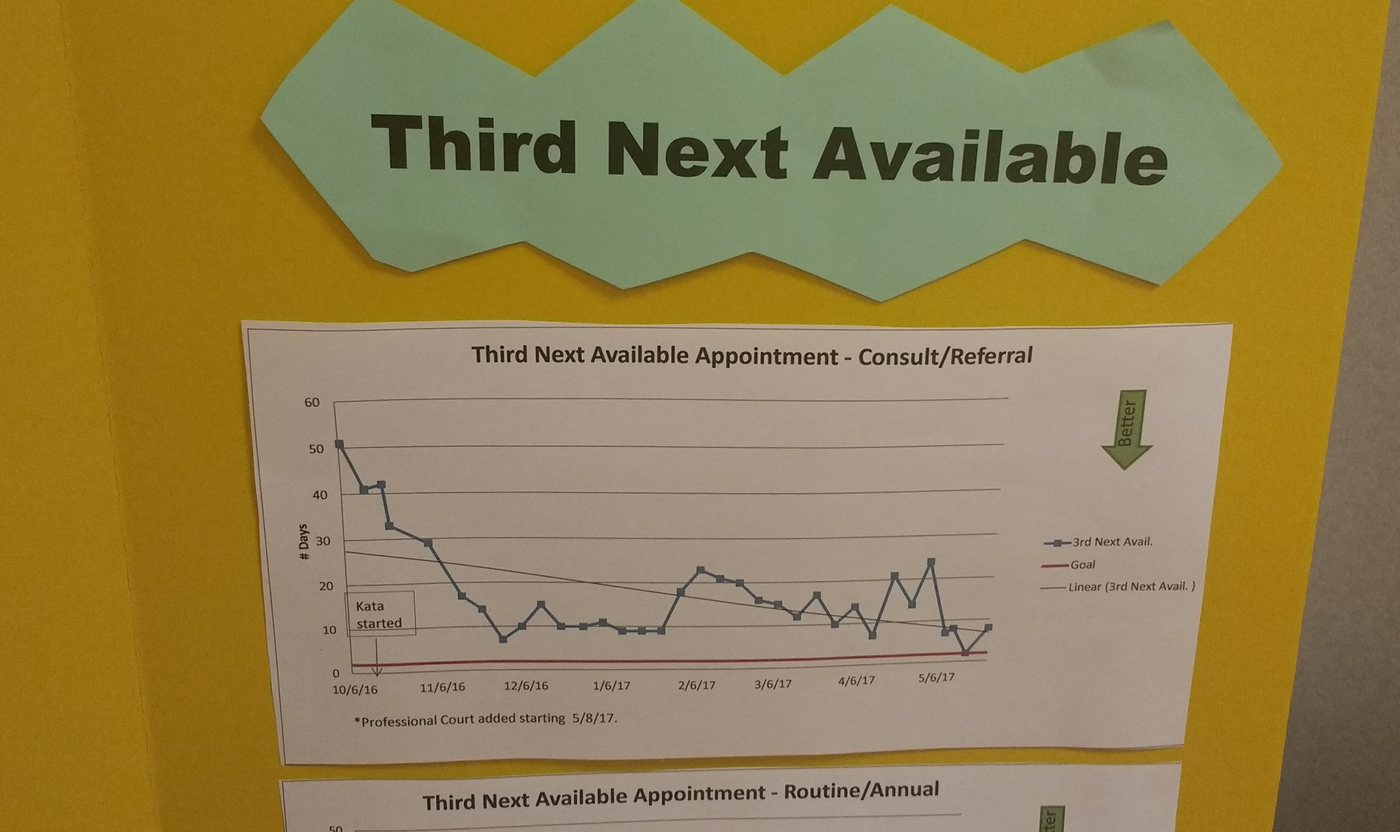
In June 2017 the health system held a poster fair. Every board on the floor was a unit team's own improvement, run through their own coaching cycles, on a problem they had chosen. None of them was a consulting engagement.
That is the only outcome worth aiming at. A transformation that produces results while the consultants are still in the building has proved nothing. One that produces a room full of teams presenting their own work, with their own charts, has proved the thing that matters.



A position, stated plainly
Build from within.
Many health systems pursue mergers and acquisitions to gain new capability. A merger produces a larger organization. It does not by itself produce a better one, and a larger organization that cannot coordinate across functions is less agile rather than more.
Traditional financial measures can mislead here, because they do not capture the value an organization actually creates or destroys. Cutting cost directly, through layoffs and inventory reduction, often raises cost over time. Improving the process lowers it, and keeps lowering it.
Our strategy is simple: build the capability internally, optimize flow, and create a seamless and genuinely better experience for providers and patients alike. Once that capability exists, evaluating outside capability becomes a real strategic choice rather than a substitute for one.
Curious how this would work on your team?
Book a discovery conversation. We will ask what you are trying to achieve and what is getting in the way, which is also how every engagement starts. Practical conversation, no sales pitch.